

Professional Introducer Sheath Selection Tips for Reliable Vascular Access
2026-11-16
Every vascular access procedure hinges on one quiet decision: which introducer sheath you reach for before the puncture even happens. Get it right and the pathway feels almost effortless; get it wrong and you invite friction, kinking, and a case that lingers longer than it should. This guide moves past generic catalog specs to the selection details that actually matter in the moment, with practical notes from INT Medical on matching sheath design to real clinical demands. If you have ever second-guessed a size, curve, or coating at the table, the next few sections will give you a sharper framework for reliable access.
Vessel Character Comes Before French Size
The habit starts early in training: pick a French size, then look for a vessel that will accept it. In practice, that order rarely survives contact with a real iliac or femoral artery. Tortuosity, calcification, recoil, and branch angles shape the procedure far more than a diameter printed on a package.
A vessel that measures wide enough on the screen can still refuse a larger sheath if the proximal bend is sharp and the wall is heavily calcified. Forcing the issue usually ends with a dissection or a stuck delivery system. Smaller, more flexible tools often track better through hostile anatomy, even when the vessel character would mathematically allow something bigger.
The practical rule is simple: read the vessel first, then choose the French size. Study the contours, the lesion length, the distal runoff, and the way contrast swirls through the lumen before committing to a device. When the vessel's behavior and the size chart disagree, the vessel wins.
Plan the Exit, Then Pick the Sheath
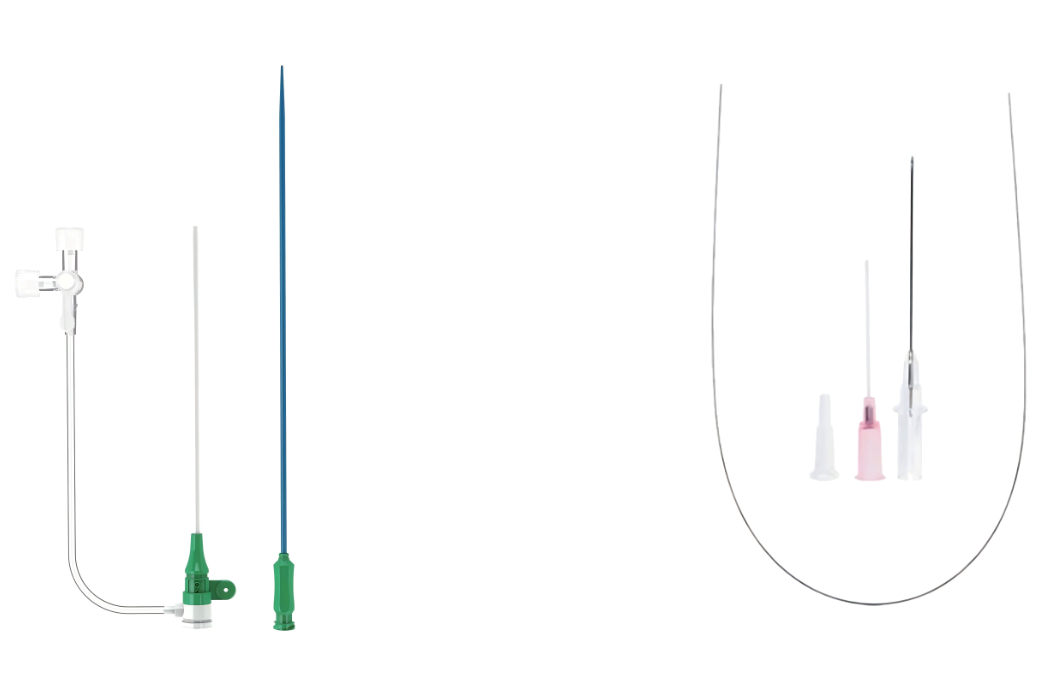
Most people pick the shape first—article, video, thread—and then hunt for an ending that fits. The more useful order is to decide where the reader should land before worrying about packaging. If the exit is a clear action, the writing can build toward that move without announcing it. If the exit is a shift in perspective, the tone can begin tilting that way early, so the final lines feel earned instead of attached.
Once the exit is clear, the sheath becomes a practical decision rather than a stylistic guess. A compact decision needs a narrow format that keeps the path visible. A slower emotional turn may need more room, not because a word count demands it, but because the idea needs space to settle. The format stops being the main event and turns into the casing that carries the point safely to the end.
The result feels quieter and more certain. Readers might not notice why the ending seems inevitable, but they will sense that the piece knew where it was headed. The sheath fits because it was chosen for the blade, not the other way around.
Dwell Time Deserves a Seat at the Decision
For years, dwell time has been treated like background noise—a metric that gets glanced at in passing but rarely invited into the room where choices are actually made. That habit quietly undermines the people who spend their days interpreting content performance. When the amount of time someone genuinely spends with a page stays on the sidelines, decisions about what to create, update, or retire drift toward shallow signals that are easier to count but far less revealing.
Giving this metric a real seat changes the conversation. Instead of asking only whether content was found, teams can ask whether it held attention long enough to matter. A short visit on a detailed guide usually means the piece did not deliver what the reader expected, while a longer stay on a well-structured article often points to relevance, clarity, and trust. Those are exactly the qualities that should guide editorial and product choices.
That does not mean treating dwell time as a single source of truth. It is most useful when placed next to context: the purpose of the page, the traffic source, the reading pattern, and the action that followed. The point is not to chase a number upward, but to make decisions that respect how people actually interact with content—slowly, selectively, and with intention.
Tip Geometry Can Undo a Perfect Puncture
A puncture can feel flawless on the surface and still fail underneath. The shape of the tip determines whether tissue separates cleanly or gets pushed, split, and torn as the shaft follows. A sharp point may slide through with very little force, but if the bevel profile creates uneven stress, the opening can become a small crack that runs beyond the intended path.
Conical tips tend to displace material radially. That looks neat from the outside but can leave crushed edges that lose their seal after the needle is withdrawn. Cutting tips, by contrast, slice first and then wedge the sides apart. On skin, a multi-bevel cutting needle can turn a round puncture into a short tear once the surrounding fibers pull back. The difference becomes obvious only after the tool exits.
What matters is the match between tip shape, entry angle, and the material being punctured. A geometry that works perfectly in one tissue can undo the result in another, not by making the puncture harder, but by changing how the wound closes around the hole. The puncture is only as good as the tip profile that leaves it behind.
Use Ultrasound to Override the Default
Most machines arrive with presets built around an average patient, an average depth, and an average scanning routine. That works until the anatomy in front of you refuses to fit the template. Instead of accepting a muddy image or working around a preset that keeps missing the target, ultrasound lets you step in and change the behavior of the system mid-exam.
This override might mean pulling the focal zone deeper, reshaping the gain curve, or switching to a lower frequency at the exact moment the default choice starts to struggle. Those adjustments are not cosmetic. They alter how the returning echoes are read, which changes what you can actually see. When you override the default deliberately, you make the machine match the tissue instead of forcing the tissue to match a factory setting.
In daily use, that saves more than time. It reduces the repeat scans that happen when a preset looks fine on the screen but fails at the bedside. The point is not to abandon automation altogether, but to recognize the moment when a manual correction will give you a cleaner answer than the default ever could.
Build a Selection Habit That Handles Variation
Most selection routines fall apart the moment conditions shift. You might have a reliable method for calm water, clear skies, or familiar terrain, but introduce a sudden change in wind, material thickness, or available tools, and the same checklist becomes useless. The goal isn't to memorize one perfect set of choices; it's to practice making selections across a range of contexts until the underlying judgment becomes automatic. Start by deliberately varying one factor at a time during training or rehearsal. Pick materials with slightly different textures, adjust the pace, or alter the sequence of operations. Each variation forces you to notice which criteria actually matter and which were just habits tied to a specific setup.
A selection habit that handles variation relies on flexible anchors rather than fixed answers. Instead of asking, “Which option is best?” train yourself to ask, “What does this situation require that the previous one didn't?” Notice the early signals: a change in resistance, an unexpected delay, a subtle mismatch in fit or feel. Those signals are not interruptions to your routine; they are the routine telling you to adjust. Over time, you build a personal library of pattern breaks. You remember what worked when the surface was uneven, when the light was low, when the sequence had to be reversed. The habit isn't about predicting every possible variation. It's about staying responsive enough that variation stops feeling like a disruption and starts feeling like information.
People often try to eliminate variation by standardizing everything around them, but that approach only works in closed environments. Real work, creative work, field work, even cooking in an unfamiliar kitchen, always introduces elements you didn't plan for. The stronger move is to intentionally expose your selection process to small, recoverable mismatches. Let the fit be slightly off, work with the less familiar tool, choose the option that forces you to compensate. What you're building is not immunity to variation but fluency within it. Over dozens of small adjustments, the selecting mind stops reaching for a single correct answer and starts reading the situation as a live set of tradeoffs. That shift in posture matters more than any specific technique, because it means each new variation becomes practice for the next one, not a threat to the habit you've built.
FAQ
A 5 Fr sheath covers most diagnostic work, but if you expect to exchange for a larger guiding catheter or use intravascular imaging, start with 6 Fr. The real rule is to match the sheath to the largest device on your table, not just the first catheter you plan to use.
Longer sheaths give you more support through tortuous iliac or subclavian segments and protect the access vessel from repeated catheter exchanges. The trade-off is a larger dead space that can dampen pressure waveforms and a higher chance of thrombus formation if flushing is inconsistent. Pick the shortest length that still reaches the stable vessel segment you need.
In tortuous or scarred access routes, yes. It lowers insertion force and reduces vessel wall trauma, which is especially useful in radial or previously dissected vessels. Just avoid repeatedly withdrawing and re-advancing the sheath through calcified plaque because the coating can wear and create embolic debris.
Check whether it seals around your smallest wire and your largest catheter without leaking during rapid exchanges. A valve that is too stiff can catch on device tips, while one that is too soft may invert or tear during removal. If you are running multiple devices through the same sheath, choose a valve designed for high exchange counts.
Switch to a reinforced or long sheath when you need to track a large device around a hostile aortic bifurcation, bypass a tortuous brachiocephalic segment, or stabilize access for mechanical thrombectomy. The added stiffness and length reduce the chance of the sheath kinking or backing out when you push bulky hardware through it.
Yes. For radial access, a slender-walled sheath of the same French size gives a smaller outer diameter at the same inner diameter, which is friendlier to the vessel and less spasmogenic. For femoral access with steep angulation, a pre-curved or kink-resistant sheath may seat better and keep flow dynamics more predictable.
Choose the shortest dwell time possible and stick to strict sterile handling rather than relying on antimicrobial sheaths alone. If you must leave one in place, check the insertion site at regular intervals, avoid unnecessary hub manipulations, and remove the sheath as soon as the clinical indication has passed.
It helps most when ultrasound guidance is already part of your access routine. An echogenic tip can confirm final position without contrast or fluoroscopy, but it should not override size, length, and valve quality. Use it as a tie-breaker when competing sheath lines are otherwise equivalent.
Conclusion
Reliable access starts with the vessel, not the catalog size. A narrow, spasm-prone radial artery will not forgive a sheath chosen solely by French dimension, so wall compliance, tortuosity, and depth should shape the initial choice before any device is opened. Once the puncture feels clean, the real test is the exit trajectory: selecting a sheath length and hub orientation that lets the wire and catheter leave the skin without kinking or crowding often matters more than the gauge itself, especially in larger patients or steep insertion angles. Dwell time adds another layer. If the line may stay for days, the sheath material, coating, and side-port configuration have to tolerate continuous movement and infusion stress rather than just a short procedure.
Tip geometry deserves attention because a supposedly perfect puncture can still be undermined by a stiff or abrupt dilator transition that strips the vessel wall or causes collapse during advancement. Ultrasound changes the default by revealing branch points, atherosclerotic plaque, and neighboring structures that palpation cannot; use that view to pick a bevel-appropriate sheath and to adjust depth in real time. Finally, a repeatable selection habit keeps variation manageable: before each case, run through the vessel character, the planned exit, the expected dwell time, and the imaging findings, then choose the introducer sheath that fits the actual anatomy instead of reaching for the usual model.
Contact Us
Contact Person: Jeffrey
Email: [email protected]
Tel/WhatsApp: 86-0633-2230056
Website: https://www.sd-intmedical.com

